
2026-10-02 岡山大学
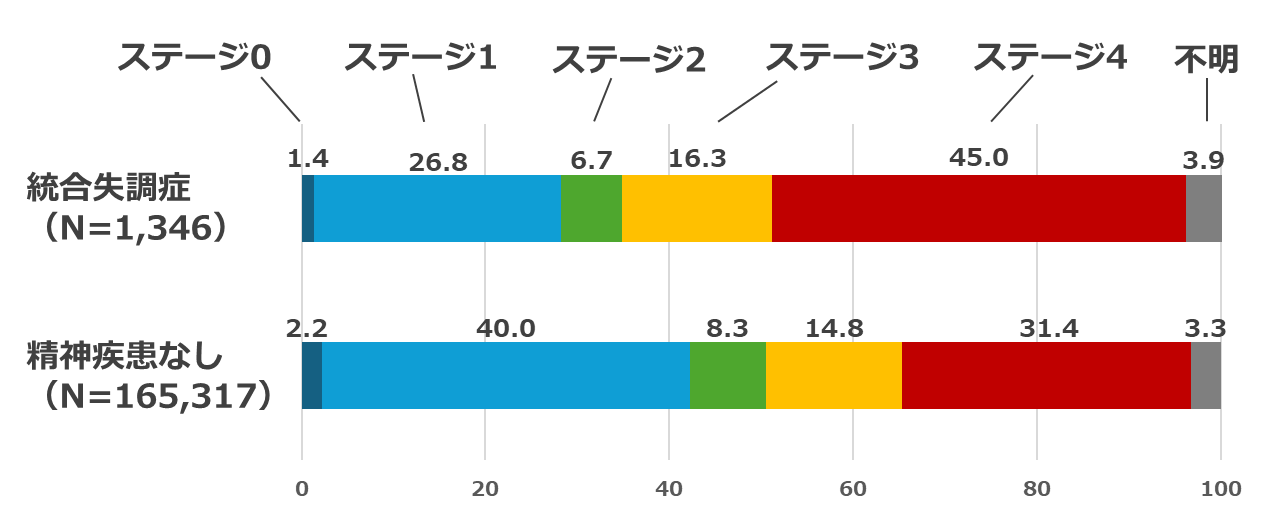
【がん診断時のステージ】
<関連情報>
- https://www.okayama-u.ac.jp/tp/release/release_id1617.html
- https://www.okayama-u.ac.jp/up_load_files/press_r8/press20261002-2.pdf
- https://journal.chestnet.org/article/S0012-3692(26)00649-5/abstract
既存の統合失調症スペクトラム障害が非小細胞肺癌の手術およびその他の治療の実施に及ぼす影響 日本における多施設共同全国コホート研究 Impact of Preexisting Schizophrenia Spectrum Disorders on the Receipt of Surgery and Other Treatments for Non-Small Cell Lung Cancer A Multicenter Nationwide Cohort Study in Japan
Yuto Yamada, MD, PhD ∙ Masaki Fujiwara, MD, PhD ∙ Taisuke Ishii, MD, PhD ∙ … ∙ Shiro Hinotsu, MD, PhD ∙ Yosuke Uchitomi, MD, PhD ∙ Masatoshi Inagaki, MD, PhD
CHEST Published:May 20, 2026
DOI:https://doi.org/10.1016/j.chest.2026.05.016
Abstract
Background
Patients with schizophrenia spectrum disorders (SSDs) experience higher cancer mortality than the general population. Disparities in treatments for non-small cell lung cancer (NSCLC) among this population remain underexamined.
Research Question
Are patients with SSDs less likely to receive surgery, adjuvant chemotherapy for stage II/IIIA, concurrent chemoradiotherapy for stage III, and systemic therapy for stage IV NSCLC compared with those without psychiatric disorders?
Study Design and Methods
This retrospective cohort study used national Hospital-Based Cancer Registry data linked to hospital-based administrative data in Japan. It included patients who received initial treatment for NSCLC between 2018 and 2021. Presence of SSDs was defined as a diagnosis using F20 to F29 codes from International Classification of Diseases, 10th Revision. The primary outcome was receipt of surgery for NSCLC. Secondary outcomes were receipt of the following: (1) adjuvant chemotherapy within 180 days in patients with pathologic stage II/IIIA NSCLC; (2) concurrent chemoradiotherapy in clinical stage III NSCLC; and (3) systemic therapy in stage IV NSCLC. Multivariable logistic regression adjusted for age, sex, clinical stage, comorbidities, and functional status was performed.
Results
The final cohort comprised 166,663 patients, 1,346 of whom had SSDs. Patients with SSDs were more likely to be diagnosed at stage IV NSCLC (45.0% vs 31.4%) and less likely to undergo surgery (31.5% vs 49.9%; adjusted OR [aOR], 0.70; 95% CI, 0.57-0.85), receive adjuvant chemotherapy (aOR, 0.31; 95% CI, 0.17-0.57), or receive systemic therapy (aOR, 0.54; 95% CI, 0.45-0.65). No significant difference was observed in concurrent chemoradiotherapy for stage III NSCLC (aOR, 0.99; 95% CI, 0.73-1.34).
Interpretation
Patients with SSDs were less likely to receive surgery and other stage-appropriate treatments for NSCLC, highlighting the need for targeted interventions to promote equitable cancer care for these individuals.
