2026-10-23 東京科学大学
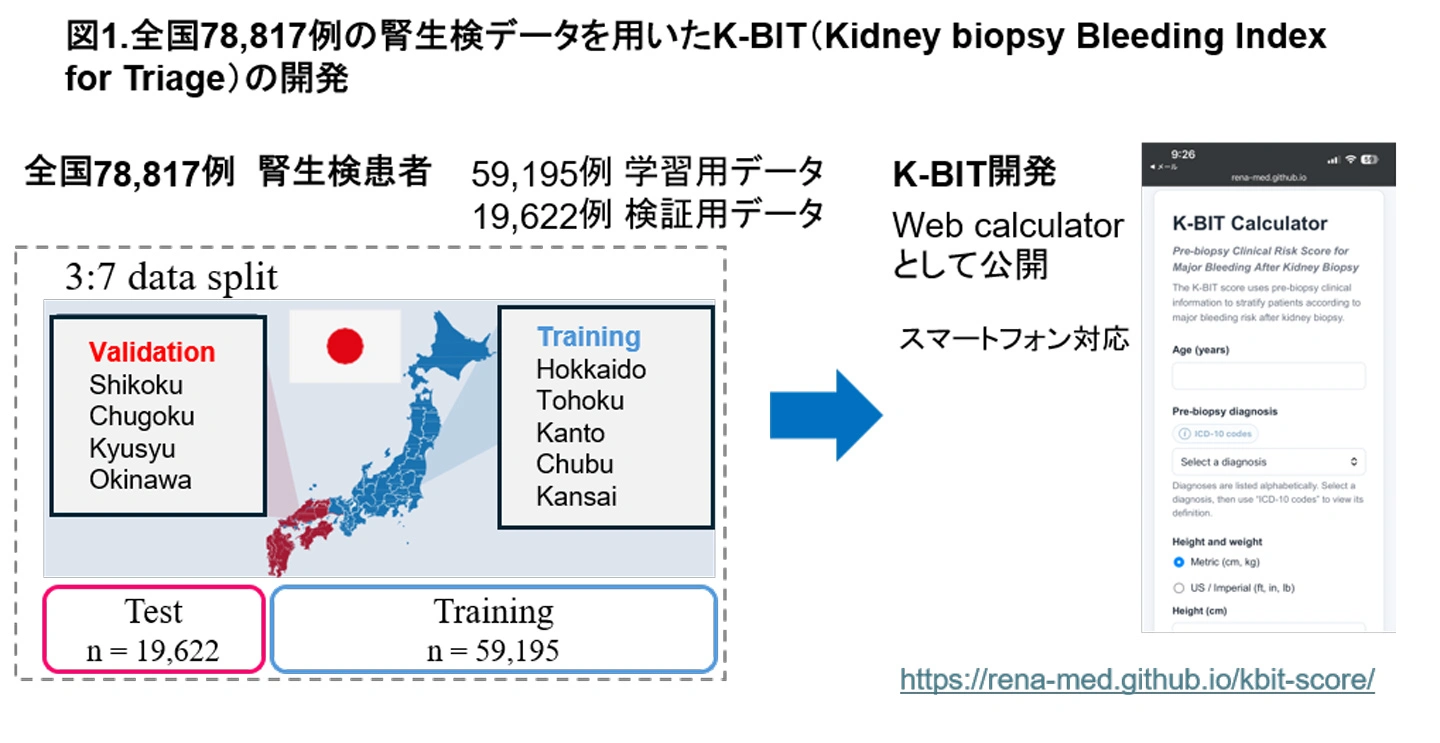
図1. 全国78,817例から開発したK-BIT(Kidney biopsy Bleeding Index for Triage)
<関連情報>
- https://www.isct.ac.jp/ja/news/89o90auvdtcp
- https://www.kireports.org/article/S2468-0249(26)03350-4/fulltext
腎生検後の重篤な出血に対する生検前臨床リスクスコアの作成 Creation of a Pre-biopsy Clinical Risk Score for Major Bleeding After Kidney Biopsy
Rena Suzukawa ∙ Daiei Takahashi ∙ Takanori Hasegawa ∙ … ∙ Kiyohide Fushimi ∙ Shinichi Uchida ∙ Shintaro Mandai
Kidney International Reports Published:September 30, 2026
DOI:https://doi.org/10.1016/j.ekir.2026.107118
Abstract
Introduction
Risk-based tools to guide care after percutaneous kidney biopsy (PKB) remain limited. We developed a simple preadmission risk score to predict post-PKB bleeding and support same-day discharge decisions, leveraging Japan’s routine inpatient observation practice.
Methods
This retrospective study included 78,817 adults undergoing native PKB, using a nationwide Japanese inpatient database (2016–2021). Risk factors for early hemostatic intervention, defined as blood transfusion or surgical or interventional hemostasis within 6 days after PKB, were evaluated using logistic and L2-penalized multinomial logistic regressions. The fitted coefficients for day 0 were discretized to develop the Kidney biopsy Bleeding Index for Triage (K-BIT), using readily obtainable prebiopsy clinical variables. The scoring was internally validated using a held-out test cohort from the same dataset.
Results
The overall bleeding rate was 1.46%. Compared with chronic glomerulonephritis, bleeding risk was higher in acute kidney injury (odds ratio [OR], 10.9; 95% confidence interval [CI], 8.55–13.9) and rapidly progressive glomerulonephritis (OR, 6.67; 95% CI 5.48–8.12). Increasing age and lower body mass index (BMI) were independently associated with higher bleeding risk. Age, prebiopsy diagnostic risk tier, BMI, and Charlson Comorbidity Index (CCI) were selected for score construction (score range, 0–9). In the validation cohort, patients with scores ≤ 2 (55.4%) had a bleeding risk of 0.37%. Simulation analysis suggested that restricting early discharge to this low-risk group could reduce hospitalization by an estimated 332 hospital days per 100 patients while maintaining low postdischarge bleeding risk.
Conclusion
Prebiopsy diagnosis, age, BMI, and comorbidities were key predictors of postbiopsy bleeding. K-BIT may support risk stratification and outpatient kidney biopsy pathways.